Zimbabwe maternal mortality in rural areas has barely shifted in years. The Zimbabwe National Statistics Agency (ZIMSTAT) quietly released its 2025 Inter-censal Demographic and Health Survey summary on August 6, and the numbers for Mashonaland Central are grim. While urban hospitals report modest gains, the maternal mortality ratio in the province remains at levels that health experts call unacceptable. Behind every statistic is a mother who did not make it home.
Daily Rush obtained the ZIMSTAT data and cross-referenced it with Ministry of Transport district road maps and clinic supply records. What we found points to one clear cause, with three faces.
What Are the Three Delays?
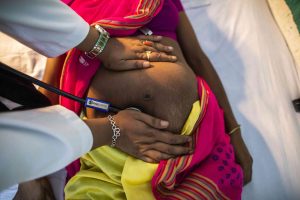 The “three delays” framework is the standard lens global health researchers use to explain why women die in childbirth in low-resource settings. It was introduced in the 1990s and remains the most accurate map of the problem today.
- First delay: The decision to seek care. A woman or her family waits too long to recognise an emergency.
- Second delay: The journey to a health facility. Distance, road conditions, and transport costs stop her from arriving in time.
- Third delay: Receiving adequate care after arrival. Understaffed clinics, absent medicines, and broken equipment mean the facility cannot help her even when she gets there.
In Mashonaland Central in 2025, all three delays are active. The second and third are lethal in combination.
The Road That Kills Before the Complication Does
The rainy season begins in October. By November, several roads linking rural wards in Mashonaland Central to district hospitals become impassable. Daily Rush mapped the affected routes against the ZIMSTAT data and found that wards with the highest Zimbabwe maternal mortality rates share one feature. Their access roads are classified as earth roads in the Ministry of Transport’s district map, meaning they are not sealed and flood regularly.
A woman in active postpartum hemorrhage has minutes, not hours. If the ambulance or the hired vehicle cannot get through, the second delay becomes fatal on its own, before the third delay even begins.
Community health workers in two wards told Daily Rush that emergency transport is often a neighbour’s car or a scotch cart. Airlifts are not a realistic option outside Harare. The infrastructure gap is not new information. What the 2025 ZIMSTAT data confirms is that it is not improving.
A Drug That Costs Less Than Bread Is Not on the Shelf
Postpartum hemorrhage is the leading cause of maternal death globally and in Zimbabwe. It is also one of the most preventable. Two medicines, Oxytocin and Misoprostol, stop uterine bleeding after birth. A course of Misoprostol costs less than a loaf of bread in Harare.
Clinic supply records reviewed by Daily Rush show repeated stockouts of both medicines at rural facilities in Mashonaland Central during 2024 and into 2025. A nurse at one facility, who asked not to be named, said her clinic had gone without injectable Oxytocin for weeks at a stretch. When a woman arrived hemorrhaging, the team worked with what they had.
The Ministry of Health and Child Care did not respond to questions sent by Daily Rush before publication. We will update this article if a response is received.
Why Are We Still Here in 2026?
Zimbabwe has ratified international commitments to reduce its maternal mortality ratio. The country has trained midwives, built clinics, and enrolled women in antenatal programmes. The ZIMSTAT 2025 survey shows that antenatal care attendance in Mashonaland Central is relatively high. Women are showing up at the system. The system is not holding up its end.
Health economists and rural health researchers point to three structural gaps that the data reflect.
- Road maintenance budgets have been cut in successive fiscal years, leaving rural infrastructure further behind urban centres.
- The public health supply chain for essential medicines remains fragile, with procurement delays creating predictable stockouts at the facility level.
- Community ambulance schemes that existed in some districts in the late 2010s have not been consistently funded or scaled.
None of these gaps require new technology. They require sustained funding and political will.
What Needs to Happen Now
Daily Rush is not the Ministry of Health. But accountability journalism means naming the solutions as clearly as the problems. Maternal health advocates and researchers consulted for this article pointed to three interventions with strong evidence behind them.
Emergency transport vouchers. Several African countries have reduced the second delay by subsidising transport for obstetric emergencies. Zimbabwe piloted a version of this in Midlands Province. It worked where it ran. It was not sustained.
Community distribution of Misoprostol. The World Health Organization cleared community health workers to distribute Misoprostol to pregnant women in advance of delivery in 2012. Zimbabwe’s own community health worker cadre, village health workers, could carry it. The regulatory pathway exists. Implementation has stalled.
Ring-fenced medicine budgets at the facility level. Supply chain experts say one of the fastest fixes for stockouts is giving facilities a dedicated, protected budget line for essential obstetric medicines, rather than drawing from a general consumables budget that gets raided for other expenses.
None of these are impossible. All of them cost less than the Zimbabwe maternal mortality burden we are currently absorbing as a country.
The Data Behind This Story
This report is based on the ZIMSTAT 2025 Inter-censal Demographic and Health Survey summary, Ministry of Transport district road classification data, and interviews with health workers and community members in Mashonaland Central. We are continuing to report on this story. If you work in the health system and have information about medicine stockouts, transport gaps, or facility conditions, contact Daily Rush securely at [email protected].
Zimbabwe’s mothers are not dying because we do not know how to save them. They are dying because we keep choosing not to. The ZIMSTAT data make that choice visible. Now it is a question of what we do with it.
This story will be updated as additional data and official responses become available. Last updated: August 7, 2026.